August 18, 2026 | Brandon Hastings
8 min read
Traumatic wounds represent a unique clinical challenge because they are rarely isolated events. Unlike the controlled environment of elective surgery, traumatic injuries are sudden, high-energy disruptions that force clinicians to pivot rapidly from life-saving stabilization to complex wound management and often challenge patients’ attitudes towards their injury.
This urgency is underscored by a sobering reality: according to the World Health Organization, traumatic injuries account for approximately 4.4 million deaths annually—nearly 8% of all deaths worldwide—positioning trauma as a primary driver of acute clinical encounters globally.
For practitioners, the complexity of these wounds often involves multiple tissue types—muscle, bone, skin—and can be complicated by systemic inflammatory responses or acute psychological shock. Further, because these injuries often occur in contaminated environments, the risk of infection and long-term morbidity is significantly higher than in elective procedures.
Consequently, successful treatment of the “whole person” across multiple, interconnected health areas requires a dual-track approach. Whether you’re a wound care specialist, emergency physician, or general practitioner, you must address the immediate physical disruption while simultaneously accounting for the systemic and psychological impact on the patient to ensure a truly successful recovery.
Keep reading to learn more about how to deliver traumatic wound care through a holistic lens and ensure a patient’s overall health.
What Is a Traumatic Wound?
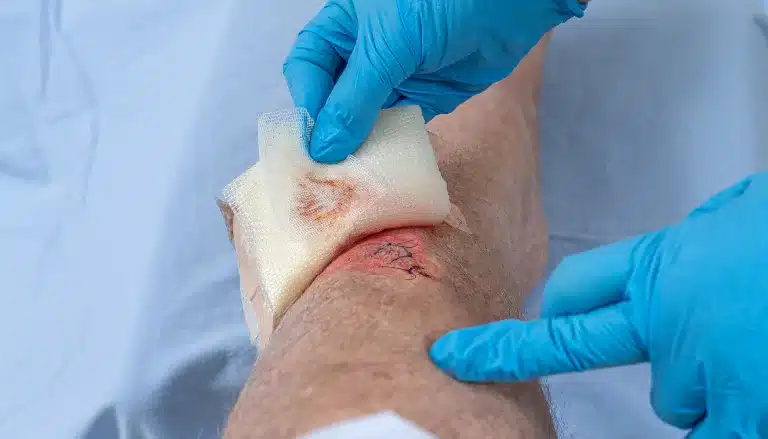
In clinical terms, a traumatic wound is any injury to the skin and underlying soft tissue that occurs suddenly due to an external force. Unlike a surgical incision, which is planned and executed under sterile conditions with precise edges, traumatic wounds can have irregular margins, varying depths, and immediate exposure to environmental contaminants.
These wounds are typically classified by the mechanism of injury, like:
- Blunt force
- Penetration
- Thermal or chemical burns
Blunt force trauma often results in abrasions or contusions, but high-velocity impact can cause significant invisible damage, such as crushing injuries that compromise blood flow to the surrounding tissue.
Degloving injuries—a severe category of blunt/shearing trauma where the skin and subcutaneous tissue are forcibly torn away from the underlying muscle and bone—represent some of the most severe traumatic wounds, often requiring extensive grafting and multidisciplinary care.
Penetrating trauma, often caused by punctures or lacerations, carries a high risk of bacterial infection deep into the fascia or muscle. Burn trauma is a special type of wound trauma that deserves its own focus. That’s why we’ve written an extensive guide on caring for these types of wounds.
Traumatic Wound Care: Back to Basics
The clinical management of a traumatic wound begins before you even directly evaluate the injury site. Following the standard ABCDE (Airway, Breathing, Circulation, Disability, Exposure) protocol is essential to ensuring that life-threatening systemic issues are stabilized before focusing on local tissue repair.
Once the patient is stable, the primary objective shifts to transforming a potentially contaminated, acute injury site into a manageable wound environment.
Preparing the Wound Bed
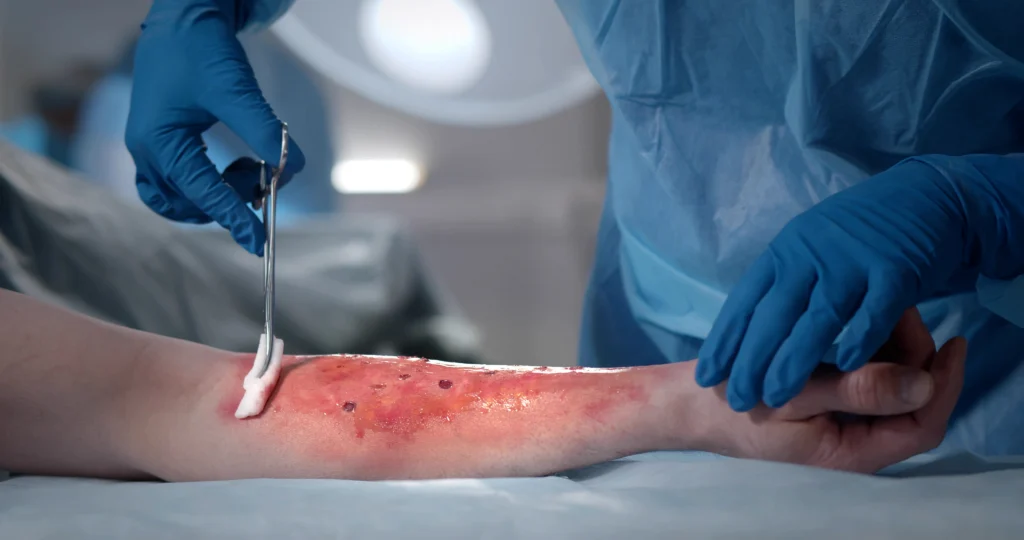
This transformation is achieved through the gold standard of trauma care: irrigation and debridement. High-pressure irrigation is sometimes necessary to dislodge foreign matter and reduce the bacterial culture , while surgical or sharp debridement removes devitalized tissue that could otherwise serve as a breeding ground for bacterial growth and infection.
Selecting Dressing and Modalities
Dressing selection in the acute phase is equally critical. For wounds with a high risk of residual contamination or those showing signs of localized infection, antimicrobial dressings (such as those containing silver or iodine) work well.
In cases of significant tissue loss or open fractures, negative pressure wound therapy (NPWT) has become a cornerstone of treatment. NPWT not only manages heavy exudate but also promotes granulation tissue formation and improves localized blood flow, which is often compromised in crushing or shearing injuries.
Determining Wound Closure
The final tactical treatment decision involves the timing of wound closure. While simple, clean lacerations may be candidates for primary closure, many traumatic wounds require more of a “wait and see” approach.
Delayed primary closure—typically performed three to five days after the initial injury— allows you to ensure the infection has been cleared and the tissue remains viable. If closure is not possible due to extensive skin loss, the wound may be left to heal by secondary intention or prepared for advanced interventions such as skin grafts or bioengineered tissue substitutes.
Managing Post-Traumatic Wound Infection Risk
The sudden, uncontrolled nature of trauma makes infection the primary threat to long-term healing. Because traumatic wounds are inherently contaminated, it’s important to not only observe the wound but also utilize clinical frameworks to identify early signs of infection before it escalates into sepsis.
Utilizing the NERDS and STONEES Criteria
In a trauma setting, differentiating between simple colonization and active infection is critical for antibiotic stewardship. The NERDS criteria (Non-Healing, Exudate, Red/Friable Tissue, Debris, and Smell) help identify localized infection that may only require topical intervention.
Conversely, the STONEES criteria (Size Increase, Temperature, Os for bone involvement, New Breakdown, Erythema, Edema, and Smell) indicate a deeper, systemic infection requiring aggressive surgical or systemic treatment. Utilizing these evidence-based markers helps tailor your intervention to the specific bacterial load of the wound.
Stewardship and Prophylactic Strategy
Managing infection risk requires a careful balance when using antibiotics. While starting antibiotics early is common for severe injuries, using them for too long can lead to resistant bacteria or other health issues.
The most important step remains source control—using physical measures to eliminate the source of infection and control ongoing contamination. Focusing on physical cleaning first and using targeted antibiotics only when necessary can lower the risk of infection from environmental contamination while still supporting the body’s natural healing process.
The Holistic View of Traumatic Wounds
Effective trauma recovery extends far beyond the edges of the wound. To achieve optimal outcomes, it’s important to look past the local injury to manage the complex interplay between the body’s systemic response and the patient’s psychological state.
Managing the Systemic Response to Injury
Because traumatic injuries trigger a systemic metabolic and inflammatory response—often characterized by a hypermetabolic state—the body’s resources are frequently diverted away from tissue repair to maintain vital organ function.
This internal stress can stall the healing process at the early inflammatory stage, which increases the risk of the wound becoming chronic or developing a secondary infection. Managing this requires a team effort where nutrition and blood sugar levels are monitored as closely as the wound itself to ensure the body has the fuel it needs for cellular repair.
Addressing the Psychological Impact of Trauma
It is also vital to recognize the mental impact that follows a sudden injury. Unlike patients who have weeks to prepare for a scheduled surgery, trauma patients are often in a state of shock.
Conditions like posttraumatic stress disorder (PTSD), anxiety, and depression are common. For example, one longitudinal study noted that 26% of trauma patients screened positive for PTSD after less than an average of 90 days following their injury. Why is this psychological component important to traumatic wound care?
Because such psychological conditions have a real physical effect on how fast a person heals, they’re crucial to understand to properly treat patients with traumatic wounds. In fact, the same longitudinal study notes that PTSD adversely affects health outcomes, including:
- Rates of rehospitalization
- Return to work
- Activities of daily living
- Perception of recovery
- Opioid use
High levels of stress hormones, like cortisol, can weaken the immune system and slow down the production of new tissue. Thus, treating the whole person means including mental health checks as a standard part of wound care.
| As the National Center for Complementary and Integrative Health (NCCIH) notes, whole person health is about “helping and empowering individuals, families, communities, and populations to improve their health in multiple interconnected biological, behavioral, social, and environmental areas” to restore health, promote resilience, and prevent diseases across their life span. |
Taking a Multidisciplinary Approach to Recovery
The best results happen when a multidisciplinary team works together. In addition to your role as wound care practitioner, the care team should include physical therapists to help with movement, nutritionists to optimize the body’s internal environment, and mental health professionals to help patients work through the emotional barriers to recovery.
By viewing a traumatic wound as one part of a larger life event, you and your fellow practitioners can better navigate the complications of trauma and help patients return to their normal lives.
Traumatic Wound: ICD-10 Coding
Accurate documentation and coding are essential for tracking trauma outcomes and ensuring appropriate reimbursement. For traumatic wounds, you’ll primarily navigate ICD-10-CM Chapter 19, which covers injuries, poisoning, and other external causes.
Unlike chronic wound coding, trauma coding requires high specificity regarding the anatomical site, the severity of the injury, and the mechanism of trauma.
To document the whole patient journey effectively, a critical component is the 7th character extension, which defines the phase of care. These are:
- A for the initial encounter
- D for subsequent encounters during recovery
- S for sequela or late effects
You must also include external cause codes to document how and where the injury occurred. This detailed level of reporting provides a clear clinical narrative that justifies the use of advanced modalities, such as NPWT or specialized debridement, while allowing for better data collection on trauma trends within a facility.
Remember that specificity in coding isn’t just a billing requirement, though that’s certainly key for operational sustainability. Specificity is also a vital part of the patient’s medical record, ensuring the complexity of their entire recovery is captured.
Advancing the Standard of Traumatic Wound Care
The clinical success of traumatic wound care depends on preventing an acute event from transitioning into a stagnant, chronic condition. While initial stabilization and surgical debridement are fundamental, long-term successful treatment requires a data-driven approach that integrates metabolic health and psychological indicators into the primary care plan.
The best patient outcomes aren’t created through reactive, localized treatments, but through the use of multidisciplinary care teams and advanced electronic health record (EHR) tools to address physical and nonphysical issues, as well as track a wound’s longitudinal narrative and anticipate complications in real time.
Ultimately, achieving superior outcomes in trauma care requires a sophisticated strategy that addresses the complex physiological disruptions caused by sudden injury, ensuring a return to functional stability for every patient.
Specialty EHRs Can Make All the Difference
See how a specialty EHR can help your staff and your patients